Author: Skypoint Recovery

alcoholic man trying to stop drinking

How to Stop Drinking: A Realistic Plan and When You Need Medical Help

If you’re thinking about how to stop drinking, you’ve already taken a hard first step, and you don’t have to figure out the rest on your own. If you drink heavily every day, please talk to a doctor before you stop. Quitting suddenly can cause dangerous withdrawal. After that, it comes down to a plan you can stick with and the right support around you. Below, we’ll cover whether to cut back or quit, a step-by-step plan, and the withdrawal signs that need medical help.

Infographic with a plan to stop drinking, alcohol withdrawal warning signs and how Skypoint Recovery can help.

Should You Cut Back or Quit Drinking?

Cutting back on alcohol can be a reasonable goal for some people. For others, quitting is the safer choice. The National Institute on Alcohol Abuse and Alcoholism’s Rethinking Drinking guide strongly advises quitting if any of these apply to you:

  • You’ve tried to cut down but couldn’t stay within the limits you set.
  • You’ve had alcohol use disorder (AUD) or have any of its symptoms now.
  • You have a physical or mental health condition that drinking causes or makes worse.
  • You take a medication that interacts with alcohol.
  • You’re pregnant or might be.

If none of those fit, talk with your doctor about which goal makes sense. Things like your age, family history, and past drinking-related injuries all matter.

Not sure whether your drinking counts as a disorder? Our guide to the difference between problem drinking and alcohol use disorder walks through the 11 symptoms doctors look for.

Your situation Better starting goal
You drink a few times a week and have no AUD symptoms Cutting back may work; set limits and track them
You’ve tried to cut back and kept going over your limit Quit, with support
You drink heavily every day or feel shaky when you stop Quit, but only with medical advice first
You’re pregnant, or drinking worsens a health problem Quit

Why Quitting Alone Is So Hard

If you’ve tried to stop drinking on your own and kept ending up back where you started, you have a lot of company. According to the 2025 National Survey on Drug Use and Health from SAMHSA, 25.7 million people ages 12 and older had alcohol use disorder in the past year. Yet only about 1 in 6 people who needed substance use treatment got it.

Excessive drinking causes about 178,000 deaths in the United States each year, according to the CDC.

A lot of people who reach out to Skypoint Recovery say the same thing: they tried to quit by themselves more than once and couldn’t make it stick. Willpower alone often falls short, because AUD changes how your brain handles cravings and stress. A clear plan and support from other people make it more likely to stick.

How to Stop Drinking: A Step-by-Step Plan

  1. Track what you drink for one week. Write down every drink before you have it. Measure your pours at home so you know what a standard drink looks like.
  2. Talk to a doctor before you stop if you drink heavily. If you drink every day, or you’ve felt shaky, sweaty, or anxious when you skip a day, get medical advice before you quit. A doctor can tell you whether you need supervised detox.
  3. Pick a quit date or set clear limits. If you’re quitting, choose a date in the next week or two. If you’re cutting back, decide how many days you’ll drink and how many drinks you’ll have, and include alcohol-free days.
  4. Clear alcohol out and avoid your triggers. Keep little or no alcohol at home. Notice the people, places, times, and feelings that make you want to drink, and plan around them.
  5. Plan for cravings before they hit. Remind yourself why you’re quitting, call someone you trust, or get busy with something else until the urge passes. Cravings usually fade if you wait them out.
  6. Have your “no” ready. Decide ahead of time what you’ll say when someone offers you a drink. A quick, polite answer makes it easier to stick with it.
  7. Line up support. Tell a friend or family member your plan. Look into support groups like AA, and ask your doctor about counseling.
  8. Ask about medication. Several FDA-approved medications can cut cravings or help you stay sober. Our post on the facts about alcohol medications explains how each one works.

Alcohol Withdrawal: Signs You Need Medical Help

If your body has gotten used to alcohol, stopping suddenly can trigger withdrawal. Symptoms often start within about 8 hours of your last drink, though they can show up days later. They tend to peak between 24 and 72 hours, and some can last for weeks.

Some withdrawal symptoms are an emergency, so it helps to know the signs ahead of time.

Symptom What it means
Shakiness, sweating, nausea, trouble sleeping Common withdrawal; call a doctor for advice
Anxiety, restlessness, a racing heart Common withdrawal; call a doctor, especially if it’s getting worse
A seizure Emergency; call 911
Seeing, hearing or feeling things that aren’t there Emergency; get medical help right away
Severe confusion or a fever Possible delirium tremens (DTs); call 911

If you drink heavily every day, don’t stop abruptly without talking to a medical provider first. A medical provider can look at your drinking and health history and tell you which level of care is right for you, from outpatient detox like the program at Skypoint Recovery to hospital care.

If you’re in crisis or thinking about hurting yourself, call or text 988 any time.

Support Options That Fit Different Needs

Detox handles withdrawal. What keeps you sober is what comes after it. Here’s how the main options compare.

Option What it gives you Good fit if
Your doctor Screening, medication, referrals You’re just starting to look at your drinking
Support groups like AA Free peer support and regular meetings You want people around you who get it
Outpatient counseling or IOP Therapy a few days a week around work or family You’re stable and can stay sober between sessions
Partial hospitalization (PHP) Several hours of therapy most days, home at night You need daily structure after detox
Medically supervised detox Medical care through withdrawal You drink heavily and get symptoms when you stop

How Skypoint Recovery Helps

Skypoint Recovery in Akron, Ohio, helps you quit drinking safely and then stay on track once the hardest days are behind you.

  • Medically supervised outpatient detox. Our medical team keeps you safe and comfortable through withdrawal.
  • Alcohol rehab. Skypoint’s alcohol rehab in Akron offers group and individual therapy, life skills training, and treatment for co-occurring anxiety, depression, and trauma.
  • PHP and IOP. You can step from several hours of therapy most days down to a flexible morning or evening schedule as you get stronger.
  • Sober living and aftercare. Our sober living homes and aftercare options, including AA and relapse prevention, keep you connected after treatment ends.

You don’t have to figure this out by yourself. Talk with someone at Skypoint about where you are with drinking, and we’ll help you choose a safe first step.

Frequently Asked Questions

Is it safe to stop drinking cold turkey?

It depends on how much and how often you drink. If you drink heavily every day, stopping suddenly can cause dangerous withdrawal, including seizures. Talk to a doctor first so you can quit with the right support.

How long does alcohol withdrawal last?

Symptoms often start within about 8 hours of your last drink and tend to peak between 24 and 72 hours. Some symptoms can go on for weeks, and sleep problems, mood swings, and fatigue can last for months.

Can you stop drinking on your own?

Some people can, especially if they drink lightly and have no withdrawal symptoms. Many people with alcohol use disorder find it much harder alone. Support groups, counseling, and treatment programs make it more likely you’ll stay sober.

What is the best way to stop drinking if you drink every day?

Start with a doctor’s visit before you stop, so withdrawal can be managed safely. From there, a detox program followed by structured treatment gives you the most support. For daily drinkers, that’s the safest answer to how to stop drinking.


man undergoing php treatment

How Long Is PHP Treatment? Typical Length and What Comes After

When people ask us about partial hospitalization, one of the first questions is how much time to set aside. PHP treatment usually lasts 3 to 4 weeks, with up to 6 hours of therapy most days, and you go home or to sober living at night. One thing we want you to know up front is that PHP is usually the first step of a longer plan. Most people move into an intensive outpatient program next, and some add sober living and aftercare. Below, we’ll cover how long PHP treatment is, what comes after it, and why the full plan takes longer than a month.

Infographic showing PHP lasts 3 to 4 weeks, followed by IOP, sober living and aftercare at Skypoint Recovery.

How Long Is PHP Treatment?

At Skypoint Recovery in Akron, partial hospitalization treatment usually lasts 3 to 4 weeks. During that time, you attend up to 6 hours of therapy on most days of the week. At night, you go home or to a sober living house.

A typical PHP day mixes group therapy, individual cognitive behavioral therapy (CBT), relapse prevention, and life skills work like managing emotions and learning about your medications. If you’re also dealing with anxiety, depression, or another mental health condition, PHP can treat both at the same time.

That said, your team checks your progress along the way, and the timing can change. Under the ASAM Criteria, the standard most treatment programs use to place patients, you should be reassessed regularly and moved to more or less intensive care based on how you’re doing. So a few things can shift your partial hospitalization program length:

  • How stable you feel day to day. Strong cravings or a recent relapse can mean a little more time at this level.
  • Co-occurring mental health symptoms. Depression, anxiety, or trauma symptoms that are still intense may need more support.
  • Your situation at home. PHP works best when you have reliable transportation and a safe, supportive place to sleep.

The Full Timeline: PHP, IOP, Sober Living and Aftercare

Here’s how the stages usually fit together. The lengths below come from Skypoint’s own program pages, and your plan may be shorter or longer.

Stage Typical length What it looks like
PHP 3 to 4 weeks Up to 6 hours of therapy, most days of the week. You live at home or in sober living.
IOP Around 10 weeks Several hours, 3 to 5 days a week, morning or evening. You live at home or in sober living.
Sober living Often a month or two, sometimes up to a year A shared sober house with peers, chores, rent and job placement
Aftercare Ongoing Support groups like AA or NA, plus life skills work, while you live at home

Add the first two stages together and you’re looking at roughly 3 months of structured treatment. Sober living and aftercare can overlap with IOP and continue after it ends.

Why Your Treatment Plan Lasts Longer Than PHP

One common surprise goes like this: someone hears “about 30 days” on the phone, assumes that’s the whole commitment, and then learns a couple of weeks in that the plan runs for months. Usually, both things were true. The 30 days described PHP. The months described the full plan, including the steps that come after it.

There’s a good reason for the longer plan. The National Institute on Drug Abuse’s Principles of Drug Addiction Treatment says most people need at least 3 months in treatment to significantly reduce or stop their drug use. The same guide notes that residential or outpatient treatment lasting less than 90 days has limited effectiveness, and that longer treatment is recommended to keep the gains you make.

You won’t spend those 3 months in full-day treatment, though. The hours drop as you get stronger, while you stay connected to care. PHP gives you a lot of support while you’re most at risk. IOP gives you room to go back to work, school, or family life while you still meet with your group several times a week. Each step gives you a chance to practice your skills in real life, then bring what’s hard back to your counselor.

If you ask about the full plan before you start, the length is much less likely to catch you off guard. Skypoint Recovery’s team can walk you through what each stage looks like for you.

What Comes After PHP: Step Down Care

Step down care means moving to a less intensive level of treatment as you get stronger. After PHP, it usually looks like this:

  1. Intensive outpatient program (IOP). You attend several hours of therapy 3 to 5 days a week, in a morning or evening block. IOP usually lasts around 10 weeks, and you can stay longer if you need it.
  2. Sober living, if home isn’t a safe place to recover yet. You live with peers who are also in recovery, follow house rules, and are encouraged to keep attending outpatient therapy. Many people stay a month or two. Our guide to how sober living works in Northeast Ohio covers the rules and what a typical day looks like.
  3. Aftercare. Support groups, 12-step meetings, and life skills work keep you connected once formal treatment ends.

PHP vs IOP: How They Compare

The biggest difference between PHP and IOP is how many hours you spend in treatment each week. IOP takes longer on the calendar because each week is lighter.

  PHP IOP
Typical length 3 to 4 weeks Around 10 weeks
Time in treatment Up to 6 hours, most days of the week Several hours, 3 to 5 days a week
Can you keep working? Usually hard to fit around a full-time job Built to fit around work, school or family
Best fit You need daily structure but not 24-hour care You’re stable and ready for more independence

For a deeper look at hours, costs, and who each level fits, see our comparison of PHP vs IOP.

Questions to Ask Before You Start PHP

Use this checklist on your first call or at intake, so you know the whole picture up front:

  • How long does PHP itself usually last for someone in my situation?
  • What does the plan look like after PHP, and how long is each stage?
  • How will my team decide when I’m ready to step down?
  • Should I live at home or in sober living while I’m in treatment?
  • What will my insurance cover at each stage?
  • When could I go back to work or school?

How Skypoint Recovery Helps

Skypoint Recovery offers each stage of this plan in Akron, Ohio, so you can step down without starting over somewhere new.

  • Partial hospitalization (PHP). Skypoint’s partial hospitalization treatment gives you up to 6 hours of therapy most days, usually for 3 to 4 weeks. It includes group therapy, individual CBT, relapse prevention, and life skills training, and it treats co-occurring mental health conditions.
  • Intensive outpatient (IOP). When you’re ready to step down, IOP lets you choose a morning or evening block 3 to 5 days a week, so you can return to work or family.
  • Sober living. Our sober living homes give you a substance-free place to live with peers, with daily chores and a job placement program.
  • Aftercare. Options include 12-step programs like AA and NA, life skills training, and the Living in Balance curriculum.

Our intake team can also help you understand what your insurance covers before you begin. If you want a clear picture of how long your plan is likely to run, ask our intake team and we’ll walk through it with you.

Frequently Asked Questions

How many hours a day is PHP?

At Skypoint, PHP includes up to 6 hours of therapy on most days of the week. That time is usually split between group sessions, individual therapy, and skills work. You go home or to sober living at the end of each day.

Can you work while in a partial hospitalization program?

Most people find it hard to keep a full-time job during PHP because of the daily schedule. Some people arrange time off work for those few weeks. Once you step down to IOP, morning or evening sessions make it easier to go back to work.

What is the next step after PHP?

For most people, the next step is an intensive outpatient program, often alongside sober living. After IOP, aftercare like support groups and life skills work keeps you connected. Your team will recommend the right step based on your progress.

How long is PHP treatment compared to IOP?

PHP usually lasts 3 to 4 weeks, while IOP usually lasts around 10 weeks. IOP runs longer because you spend fewer hours in treatment each week. Together, they often add up to about 3 months of care.

man experiencing weed withdrawal

Weed Withdrawal Symptoms: What to Expect, How Long It Lasts, and When to Get Help

Weed withdrawal symptoms can show up as a short temper, a restless, anxious feeling and trouble sleeping, usually a day or two after you stop. It’s most common in people who’ve been using every day or close to it. For most, the first week is the hardest. It usually isn’t dangerous, but the bad sleep and low mood are a big reason people go back to using. Below, we’ll cover what to expect, how long it lasts, and when to get support.

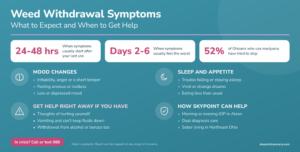
weed withdrawal symptoms infographic

Common weed withdrawal symptoms

If you’ve been using for a while, your brain has gotten used to having THC around. When it’s suddenly gone, your mood, sleep and appetite take a little time to settle back down. The National Institute on Drug Abuse lists these as the most common symptoms:

  • Irritability, anger or a short temper
  • Feeling nervous, anxious or restless
  • Low or depressed mood
  • Trouble falling asleep or staying asleep
  • Strange, vivid or unsettling dreams
  • Eating less than usual, sometimes with weight loss
  • Headaches, sweating, stomach pain or shakiness

Cravings come along with most of these. You might notice them most at the times of day you used to smoke, vape or take an edible.

You don’t need to have every symptom for it to count as withdrawal. Some people mostly struggle with sleep and mood. Others notice the irritability first, usually because the people around them point it out.

Weed withdrawal timeline: how long does it last?

Symptoms usually start within 24 to 48 hours after your last use and peak somewhere between days 2 and 6. For most people, the worst of it eases within about two weeks. If you were a heavy user, sleep trouble and some mood symptoms can hang on for three weeks or longer.

When What’s common What helps most
Days 1 to 2 Irritability, cravings, trouble falling asleep Clear out your supply and plan your evenings
Days 2 to 6 (peak) Poor sleep, vivid dreams, anxiety, low appetite, headaches Regular meals, a set bedtime, someone to check in with
Week 2 Most symptoms fade, cravings come and go Keep the new routine going, avoid old triggers
Week 3 and beyond Sleep and mood can still be off for heavy users Talk to a professional if it isn’t improving

Several things can make withdrawal stronger or longer:

  • How much and how often you used. Daily use and larger amounts usually mean a harder first week.
  • How strong your products were. THC levels in illegal cannabis seized by law enforcement roughly quadrupled between 1995 and 2022, and some dispensary flower and concentrates top 40% THC.
  • Other substances. People who also smoke cigarettes or use other drugs tend to have a rougher time.
  • Your mental health. If you were using weed to manage anxiety, depression or sleep problems, those can come back when you stop.

Is it weed withdrawal or something else?

Not every symptom after quitting is withdrawal. This table can help you sort out what you’re feeling and what to do next.

What you notice What it might be What to do
Irritability, poor sleep and low appetite that start 1 to 2 days after stopping and fade over 1 to 2 weeks Weed withdrawal Ride it out with a plan, and get support if you keep going back
Repeated nausea, vomiting and belly pain while you’re still using heavily, often eased by hot showers Cannabinoid hyperemesis syndrome (CHS) See a doctor, and get care right away if you can’t keep fluids down
Anxiety, depression or insomnia that was there before you started, or that gets worse after a few weeks An underlying mental health condition Get an assessment so both issues can be treated together

That last row is more common than people expect. If it sounds like you, take a look at these signs you might need dual diagnosis treatment. At Skypoint Recovery Ohio, our team treats substance use and mental health at the same time, so you don’t have to figure out which one came first before getting help.

What weed use looks like in Ohio right now

Since Ohio voters legalized adult-use cannabis in 2023, more Ohioans are using it, and many of them are trying to cut back. In a statewide poll of 2,000 Ohio adults from the OneOhio Recovery Foundation, taken in early 2026:

  • 41% of Ohio adults said they currently use marijuana in some form.
  • 47% of people who use said they use at least once a day.
  • 52% of current users said they had tried to stop.

So if you’ve tried to quit and ended up back where you started, you’re in very common company. Nationally, the 2025 National Survey on Drug Use and Health found that 19.3 million people aged 12 or older had a marijuana use disorder, the most common drug use disorder in the country. Withdrawal is one of the signs of that disorder, and it’s often the part that makes quitting on your own so hard.

How to get through weed withdrawal

There’s no FDA-approved medication for cannabis withdrawal, so getting through it comes down to planning, support and taking care of the basics. These steps help most people:

  1. Pick your approach. Some people step down over a week or two. Others find a clean stop easier. Either can work, as long as you have a plan for days 2 to 6.
  2. Clear out your supply. That includes vapes, edibles and anything stashed in the car.
  3. Protect your sleep. Keep the same bedtime, cut caffeine after noon and put your phone away before bed. Expect vivid dreams for a while.
  4. Eat even if you’re not hungry. Small, regular meals and plenty of water help with mood and headaches.
  5. Move your body. A walk, a workout or time outside can take the edge off restlessness.
  6. Change the routines tied to using. Learning your internal and external triggers makes the hardest moments easier to see coming.
  7. Tell someone. A friend, family member, sponsor or support group can check in on the tough days.

Try not to swap weed for alcohol or sleeping pills to get through it. That can trade one problem for another.

When weed withdrawal means it’s time for more support

Withdrawal from weed alone usually isn’t medically dangerous. Still, it’s worth talking to a professional if:

  • You’ve tried to quit several times and gone back within days.
  • You were using weed to cope with anxiety, depression, trauma or sleep problems, and those are coming back strong.
  • Your mood is getting worse instead of better after the first couple of weeks.
  • You’re also drinking or using pills like benzodiazepines. Stopping those can be dangerous, and we can help you arrange medically supervised detox through one of our partner facilities.
  • Weed is causing problems at work, at home or in your relationships.

If you’re having thoughts of hurting yourself, call or text 988 to reach the Suicide & Crisis Lifeline right away. It’s free and open 24/7.

Behavioral therapies such as cognitive behavioral therapy (CBT) and motivational enhancement therapy can be effective for cannabis use disorder. They teach you how to handle cravings, stress and the situations that used to lead to using.

How Skypoint Recovery Ohio helps

At our Akron treatment center, we work with people from across Northeast Ohio who are ready to cut back or stop using cannabis and want real support while they do it.

  • Intensive outpatient treatment. Our intensive outpatient program with morning or evening sessions meets for several hours, three to five days a week. You’ll work through group and individual therapy, including CBT, and keep up with work and family.
  • More structure when you need it. In our partial hospitalization program (PHP), you attend up to six hours of therapy most days and go home or to sober living at night.
  • Dual diagnosis care. If anxiety, depression or trauma is part of the picture, we treat it alongside your cannabis use.
  • Sober living. Our sober living homes throughout Northeast Ohio give you a peer-led, substance-free place to live while you’re in treatment.

Skypoint accepts Medicaid, and our team can check your coverage before you commit to anything. The first step is just a conversation about what’s going on. After that, we’ll do an assessment and build a plan around your needs. Not sure where to start? Call 330-919-6864 or send our team a confidential message, and we’ll get back to you.

Frequently asked questions

1. How long does weed withdrawal last?

Most symptoms start within a day or two, peak around days 2 to 6, and ease within about two weeks. If you used heavily for a long time, sleep problems and mood changes can last three weeks or more. If you’re still struggling after a month, it’s a good idea to talk with a professional.

2. Can weed withdrawal cause nausea or headaches?

Yes. Headaches, stomach pain, sweating and shakiness are all possible, though mood and sleep symptoms are more common. Repeated vomiting while you’re still using heavily may be cannabinoid hyperemesis syndrome instead, which needs medical care.

3. Is weed withdrawal dangerous?

For most people it’s uncomfortable but not dangerous. The bigger risks are going back to using, or swapping in alcohol or pills to cope. Get help right away if you have thoughts of hurting yourself or you’re also withdrawing from alcohol or benzodiazepines.

4. Does Medicaid cover treatment for marijuana use in Ohio?

Skypoint Recovery Ohio accepts Medicaid. When you call 330-919-6864, our admissions team can check your coverage and talk through which level of care fits, from IOP to PHP and sober living.

When you’re ready, we’re here. You don’t have to wait until things fall apart, and you don’t have to quit on your own. Call our Akron team at 330-919-6864 any time for a free, confidential conversation about what you’re going through, or email admissions@skypointrecovery.com. Your Journey, Our Commitment.

Methadone Withdrawal Symptoms: What to Expect and How to Taper Safely

Methadone withdrawal symptoms can start when you lower your dose or stop after taking it regularly. It often feels like a bad flu: aches, restlessness, sweating, an upset stomach, and poor sleep. Because methadone stays in your body a long time, symptoms build more slowly than with heroin or fentanyl, and they can last longer. The biggest risk comes afterward: once your tolerance drops, going back to opioids can cause an overdose. Below, we’ll cover what to expect, how a safe taper works, and how to protect yourself.

methadone withdrawal symptoms infographic

Why Methadone Withdrawal Is Different

Methadone is a long-acting opioid. It’s used to treat opioid use disorder, and sometimes for pain. The FDA label for Dolophine (methadone) puts its elimination half-life at 8 to 59 hours. That long, steady presence is what makes it useful in treatment. It also shapes withdrawal.

Because methadone stays in your body so long, withdrawal usually starts later and lasts longer than heroin withdrawal. According to MedlinePlus, symptoms usually begin within 12 hours of the last heroin use but within 30 hours of the last methadone dose. Here’s a general comparison:

Heroin Methadone
When withdrawal usually starts Within 12 hours of the last use Within 30 hours of the last dose
How long it lasts Usually eases within 3 to 5 days Peaks around day 3, then fades gradually over 3 weeks or longer

Common Methadone Withdrawal Symptoms

Common withdrawal symptoms include:

  • Restlessness and yawning
  • Watery eyes and runny nose
  • Sweating and chills
  • Muscle aches and enlarged pupils

Other symptoms can develop too:

  • Irritability and anxiety
  • Back pain, joint pain, and weakness
  • Stomach cramps, nausea, vomiting, and diarrhea
  • Poor appetite and trouble sleeping
  • Higher blood pressure, faster breathing, and a faster heart rate

Opioid withdrawal can be very uncomfortable, but it is not life-threatening on its own. It still carries real risks, though, including dehydration from vomiting and diarrhea, and what happens if you return to opioids.

The Real Danger: Losing Your Tolerance

Withdrawal fades, but your tolerance fades with it. Anyone who hasn’t taken opioids for more than 5 days may no longer be tolerant. After a taper or an abrupt stop, a dose you used to handle can slow your breathing enough to kill you.

The risk of relapse after stopping methadone maintenance is also high. And with fentanyl so common in the drug supply, a relapse can be especially dangerous. In Ohio, methadone was involved in 110 unintentional overdose deaths in 2023, while fentanyl and its analogs were involved in 78% of all overdose deaths in the state, according to the Ohio Department of Health’s 2023 overdose report.

If you’re tapering, or you’ve recently stopped:

  • Keep naloxone (Narcan) where you and the people around you can reach it. It’s worth talking about naloxone access with your prescriber whenever methadone is started or renewed.
  • Tell someone you trust that your tolerance is lower now.
  • Have a plan for cravings before they hit.

How to Taper Off Methadone Safely

Stopping methadone suddenly is not recommended. For people on methadone maintenance, the recommended pace is specific: dose reductions should generally be less than 10% of the maintenance dose, with 10 to 14 days between each reduction.

At that pace, a full taper usually takes months. A safe taper:

  • Is planned with your opioid treatment program (OTP), where methadone for opioid use disorder is dispensed
  • Moves in small steps, with room to pause or slow down if symptoms get hard to manage
  • Comes with counseling and a relapse-prevention plan
  • Answers the question “Is now the right time?” first. Stopping maintenance carries a high risk of relapse, so that’s a decision to make with your provider.

When to Get Extra Support

Consider more support than your usual clinic visits if:

  • You’ve tried to taper before and relapsed
  • You’re thinking about stopping on your own
  • You also use alcohol, benzodiazepines, or stimulants
  • You’re dealing with depression, anxiety, or trauma alongside opioid use

How Skypoint Recovery Helps

At Skypoint Recovery in Akron, our medically supervised opiate detox helps you manage withdrawal safely, and our detox services include medication-assisted treatment. After detox, our PHP in Akron and intensive outpatient program keep structure and support in place as you settle into recovery. Learn more about how medication-assisted treatment fits into recovery.

If you’re thinking about coming off methadone, you don’t have to plan it alone. Talk with our team about your options confidentially.

Frequently Asked Questions

1. How long does methadone withdrawal last?

It usually lasts longer than heroin withdrawal. Methadone withdrawal can fade gradually over 3 weeks or longer, while heroin withdrawal tends to ease within a few days.

2. When does methadone withdrawal start?

Later than with heroin. Symptoms usually start within about 30 hours of the last methadone dose, compared with about 12 hours for heroin.

3. Can methadone withdrawal kill you?

Opioid withdrawal is not life-threatening by itself, though vomiting and diarrhea can cause dehydration. The bigger risk is overdose if you use opioids again after your tolerance drops.

4. How fast can you taper off methadone?

The recommended pace is dose reductions of generally less than 10%, with 10 to 14 days between each one. Your opioid treatment program can adjust the pace to how you’re doing.

Vyvanse Withdrawal: Symptoms, How Long It Lasts, and How to Stop Safely

Vyvanse withdrawal can happen when you stop or cut back on Vyvanse (lisdexamfetamine) after taking it for a while. You might feel tired, down, and hungrier than usual, sleep more or less than normal, and have vivid, unpleasant dreams. It usually isn’t physically dangerous, but the low mood can hit hard, and it’s easy to mistake for your ADHD coming back. Below, we’ll cover what to expect, how long it lasts, and how to stop safely.

vyvanse withdrawal infographic

Why Vyvanse Withdrawal Happens

Vyvanse is a prodrug. Your body converts it into dextroamphetamine, a stimulant that raises dopamine and norepinephrine in the brain. That boost helps with focus in ADHD and with binge eating disorder, the two conditions it’s approved to treat. With daily use, your brain adapts to having that extra stimulation. When it’s taken away, your energy, mood, and motivation can dip below your normal baseline for a while.

The 2026 Vyvanse prescribing information is clear that the drug carries a high potential for misuse, which can lead to a substance use disorder. It can also cause physical dependence with repeated use, which is why stopping or cutting back can bring on withdrawal.

Vyvanse Withdrawal Symptoms

Withdrawal signs after stopping or lowering the dose following long-term use include:

  • Low mood (dysphoria) and depression
  • Fatigue
  • Vivid, unpleasant dreams
  • Sleeping much more than usual, or not being able to sleep
  • Increased appetite
  • Feeling slowed down, or feeling agitated

Anxiety and trouble concentrating can show up too.

When to get help right away

Call or text 988 if you have thoughts of suicide or self-harm. Reach out to your prescriber or a treatment team if your mood keeps sinking instead of lifting, or if you find yourself taking extra doses to avoid the crash.

How Long Does Vyvanse Withdrawal Last?

Vyvanse turns into dextroamphetamine, which has a half-life of about 10 to 11 hours in healthy adults, so the amount in your body drops steadily once you stop. From there, according to SAMHSA’s guide to treating stimulant use disorders, stimulant withdrawal generally follows this pattern:

  • Within hours to days: symptoms usually begin after prolonged, heavy use stops.
  • The first several days: the most severe symptoms tend to hit, then start to ease.
  • One to three weeks: milder symptoms, such as fatigue, low mood, anxiety, and trouble concentrating, can hang on.

For some people, depression, anxiety, and sleep problems last weeks to months. Withdrawal usually develops after prolonged, heavy use, so the dose you took and how long you took it both shape what you feel.

Is It Withdrawal or Your ADHD Coming Back?

Some of what you feel after stopping is withdrawal. Some of it is the condition Vyvanse was treating. Knowing which is which helps you and your prescriber decide what to do next.

Usually withdrawal Usually ADHD returning
Heavy fatigue and sleeping far more than usual Trouble focusing that was there before you started Vyvanse
Low mood, flatness, vivid dreams Restlessness and impulsivity at your old baseline
Big appetite changes Symptoms that stay steady rather than fading
Tends to ease over days to weeks Doesn’t improve with time off the medication

If you took Vyvanse for binge eating disorder, returning urges to binge can feel like withdrawal too. Tell your prescriber so they can plan for it.

How to Stop Vyvanse Safely

The safest way to stop is with a plan made alongside your prescriber:

  • Don’t stop on your own if you’ve taken high doses or used it for a long time. Ask whether stepping the dose down makes sense for you.
  • Plan for the first week. Clear your schedule where you can, and expect to need more sleep.
  • Keep meals regular, since appetite often jumps.
  • Track your mood daily so you can spot depression that’s getting worse.
  • Have a plan for your ADHD or binge eating symptoms, whether that’s another treatment, therapy, or practical supports.

If you’ve been misusing Vyvanse

Taking more than prescribed, crushing capsules, or using someone else’s prescription changes the picture. At that point, stopping means treating a stimulant use disorder as well as ending a medication. Therapy and structured support help most in the weeks after the crash, when cravings and low mood can hang on.

How Skypoint Recovery Helps

At Skypoint Recovery in Akron, our mental health Intensive Outpatient Program offers morning or evening sessions three to five days a week, so you can get support for your mental health while you keep up with daily responsibilities like work or school. If you need more support day to day, our partial hospitalization program offers a higher level of care. When stimulant misuse and mental health struggles show up together, our dual diagnosis care treats both.

Still weighing whether Vyvanse is right for you? Our guides to Vyvanse side effects and Vyvanse vs. Adderall cover what to know. When you’re ready to talk, contact our team for a confidential conversation.

Frequently Asked Questions

1. How long does Vyvanse withdrawal last?

Symptoms usually begin within hours to days of stopping, and the most severe ones tend to ease after several days. Milder symptoms can last one to three weeks, and for some people, depression, anxiety, or sleep problems last weeks to months.

2. What does Vyvanse withdrawal feel like?

Most people feel tired, flat, and unmotivated. Sleep changes, vivid dreams, a bigger appetite, and low mood are common.

3. Can you stop Vyvanse cold turkey?

Decide that with your prescriber. After high doses, long-term use, or misuse, a planned approach is safer because of the risk of depression.

4. Is Vyvanse withdrawal dangerous?

It usually isn’t physically dangerous. The main risk is depression, so get help right away if you have thoughts of suicide.

cocaine addict experiencing withdrawal

Cocaine Withdrawal: Symptoms, Timeline, and How to Get Through the Crash

Cocaine withdrawal can start within hours of your last dose if you’ve been using regularly. You’ll usually feel exhausted and low, sleep a lot, eat more than usual, and have strong cravings. Physically, it’s rarely as dangerous as alcohol or benzodiazepine withdrawal. Still, the depression and cravings can be intense, and they’re the main reason people go back to using. Below, we’ll cover what to expect and what actually helps.

cocaine withdrawal infographic

Why Cocaine Withdrawal Happens

Cocaine causes dopamine, the chemical tied to reward and motivation, to build up in the brain. With repeated use, the brain adapts, and its reward system becomes less responsive to everyday pleasures. NIDA explains that the brain’s stress circuits also become more sensitive over time, so you feel worse than normal when you’re not using. When the cocaine stops, you’re left with a reward system that’s running low and a stress system that’s running high.

Common Cocaine Withdrawal Symptoms

Withdrawal most often hits people who have used a lot of cocaine and then cut down or stop, according to MedlinePlus. It often shows up as:

  • Extreme tiredness and sleepiness
  • Low mood, or losing pleasure in things you used to enjoy
  • Feeling hungrier than usual
  • Irritability and restlessness
  • Strong cravings for cocaine

Physically, it’s usually less dangerous than withdrawal from alcohol. The bigger risks are emotional. The depression can be deep, and some people have suicidal thoughts during withdrawal.

When to get help right away

Call or text 988 if you or someone you love has thoughts of suicide or self-harm. Call 911 for any medical emergency. If your mood keeps sinking, take it seriously, even if it seems like “just the crash.”

How Long Does Cocaine Withdrawal Last?

In people who have used heavily, the crash can begin almost right away after they stop. From there, cravings and depression can last for months after long-term heavy use, though symptoms usually fade over time.

A helpful way to think about it:

Phase What it can feel like
The crash Exhaustion, sleepiness, hunger, low mood, and strong cravings soon after heavy use stops.
The following weeks Low mood, anxiety, sleep problems, and cravings can hang on.
The months after Cravings and depression can linger, and stress or reminders of using can set off cravings.

The longest-lasting cravings and low mood tend to follow long-term heavy use, and that long tail is why support after the crash matters as much as getting through it.

Why the Ohio Numbers Make This Urgent

In 2023, cocaine was involved in 1,738 unintentional overdose deaths in Ohio, 39% of the state’s total and a 7% increase from 2022, according to the Ohio Department of Health’s 2023 overdose report.

Much of that risk comes from what’s in the supply. Cocaine is sometimes mixed with fentanyl, and that contamination is a major driver of overdose deaths. If you don’t regularly use opioids, your tolerance to them is low, so one relapse during a hard stretch of withdrawal can be deadly. That’s a big reason to get support during this window instead of white-knuckling it.

What Helps During Cocaine Withdrawal

There are currently no FDA-approved medications for cocaine use disorder. What does work is structured behavioral care:

  • Cognitive behavioral therapy (CBT) helps you spot the situations where you’re most likely to use and practice what to do instead.
  • Contingency management rewards you for staying drug-free, usually with vouchers or prizes. It’s one of the effective behavioral treatments for cocaine use.
  • Structured outpatient care, such as a partial hospitalization program, builds that therapy into your week. For most people, outpatient care works as well as inpatient care.

At home, a few basics make the crash easier to ride out:

  • Sleep as much as your body asks for in the first days.
  • Eat regular meals, even if your appetite swings.
  • Tell one trusted person what you’re going through.
  • Cut contact with people you used with and delete dealer numbers.
  • Plan for your highest-risk times of day before they arrive.

How Skypoint Recovery Helps

At Skypoint Recovery in Akron, our partial hospitalization (PHP) program gives you several hours of treatment a day while you live at home or in sober living. That structure helps in the weeks after the crash, when low mood and cravings can hang on. If low mood or anxiety was part of the picture before cocaine, our team treats both together. See the signs you might need dual diagnosis treatment to learn more.

When you’re ready, get in touch with our team for a confidential conversation about next steps.

Frequently Asked Questions

1. Does cocaine have withdrawal?

Yes. People who have used a lot of cocaine often go through withdrawal when they cut down or stop. It’s mostly mental and emotional: exhaustion, depression, increased appetite, and cravings.

2. How long does cocaine withdrawal last?

The crash can start almost right away. After long-term heavy use, cravings and depression can last for months, though symptoms usually fade over time.

3. What is cocaine withdrawal like?

It often feels like a crash: sleepiness, exhaustion, low mood, and a bigger appetite. Cravings can be intense, and the low mood can feel like depression.

4. Is cocaine withdrawal dangerous?

It’s usually not physically dangerous the way alcohol withdrawal can be. The main risks are severe depression, suicidal thoughts, and relapse, which is especially risky now that cocaine can contain fentanyl.

Xanax Withdrawal Symptoms: Timeline, Dangers, and Why Medical Detox Matters

Xanax withdrawal symptoms can show up when you cut back or stop taking Xanax after using it regularly. Most people notice anxiety, trouble sleeping, and shakiness, and in serious cases it can lead to seizures or hallucinations. Because Xanax leaves your body quickly, symptoms can start sooner than you’d expect, and stopping suddenly can be life-threatening. Below, we’ll cover what withdrawal feels like, how long it lasts, and how to get off Xanax safely.

xanax withdrawal symptoms infographics

Why Xanax Withdrawal Happens

Xanax (alprazolam) is a benzodiazepine. It calms the brain by boosting GABA, the chemical that slows nerve activity. When you take it every day, your brain adjusts and starts relying on it. Take it away quickly and your brain has to readjust without it, which is what brings on withdrawal.

This is physical dependence, and it can happen even when you take Xanax exactly as prescribed. People who take higher doses, or take it for longer, are at greater risk of withdrawal reactions. For many people, the risk of significant withdrawal starts after one to three months of regular use at moderate to high doses.

Common Xanax Withdrawal Symptoms

Withdrawal can bring a mix of mental and physical symptoms, including:

  • Anxiety, panic attacks, irritability, and restlessness
  • Trouble sleeping
  • Headache, dizziness, and fatigue
  • Nausea, vomiting, diarrhea, and loss of appetite
  • Tremor, muscle pain, and stiffness
  • A racing heart and higher blood pressure
  • Sensitivity to light and sound
  • Blurred vision, poor memory, and feeling detached from yourself or your surroundings

Many of these feel like the anxiety Xanax was treating in the first place, so it can be hard to tell withdrawal apart from the original problem.

Dangerous symptoms that need emergency care

Severe reactions can also happen, including seizures, hallucinations, delirium, psychosis, catatonia, mania, and suicidal thoughts. Call 911 or go to the nearest emergency room if you or someone you love has a seizure, becomes confused, or sees or hears things that aren’t there. If you’re having thoughts of suicide, call or text 988.

How Long Does Xanax Withdrawal Last?

There’s no single timeline, since dose, how long you’ve taken it, and your health all change it. What is well established:

  • It can start quickly. Alprazolam has an average half-life of about 11 hours, so levels in your body drop fast once you stop.
  • The acute phase comes first. Stopping suddenly or cutting the dose fast can trigger acute withdrawal reactions in this phase, including seizures, and these can be life-threatening.
  • Some symptoms can linger. Protracted withdrawal symptoms, such as anxiety, trouble thinking, and sleep problems, may last weeks to more than 12 months.

A gradual taper won’t always prevent every symptom, but it lowers your risk of withdrawal reactions, including the dangerous ones.

What a Safe Xanax Taper Looks Like

A taper lowers your dose in planned steps instead of stopping all at once, and the guidance on how fast to go is fairly specific. The FDA prescribing label for Xanax says to lower the dose by no more than 0.5 mg every 3 days. A newer tapering guideline from the American Society of Addiction Medicine and nine other medical groups favors a much slower, more personalized pace.

Taper detail Recommended pace
Fastest label pace Reduce by no more than 0.5 mg every 3 days. Some people need to go slower.
Newer starting pace Cut the dose by 5% to 10% every 2 to 4 weeks.
Newer upper limit Don’t exceed a 25% cut every 2 weeks.
Total time Months to years for someone who has used a high dose for a long time.

Whatever the pace, benzodiazepines should never be stopped abruptly in someone who is likely dependent.

In practice, a good taper:

  • Follows a written plan from your prescriber, adjusted to how you feel
  • May start by switching from Xanax to a longer-acting benzodiazepine such as clonazepam, which is worth discussing with your prescriber
  • Pauses or slows down when symptoms get hard to manage instead of pushing through
  • Treats the anxiety or sleep problem underneath, so there’s something in place when the Xanax is gone
  • Includes a plan for cravings and relapse if you’ve been taking more than prescribed

Why Mixing Xanax With Other Drugs Raises the Stakes

Xanax is especially risky with opioids, since the combination can slow your breathing to a dangerous degree. You should also avoid alcohol and other sedating drugs while taking it. In Ohio, benzodiazepines were involved in 375 unintentional overdose deaths in 2023, 8% of the state’s total and a 4% increase over 2022, based on the Ohio Department of Health’s 2023 overdose report. If you use Xanax alongside other substances, it’s much safer to go through withdrawal and recovery with medical oversight.

When to Consider Medical Detox

A supervised setting makes sense if any of these apply to you:

  • You take a high dose, or you’ve taken Xanax daily for months
  • You’ve tried to cut back before and couldn’t
  • You take more than prescribed, or buy pills outside a pharmacy
  • You also use alcohol, opioids, or other drugs
  • You’ve had a seizure, or severe anxiety or depression, in the past

Buying pills outside a pharmacy carries its own danger. Many fake pills are made to look like Xanax but contain fentanyl, and some hold a potentially lethal dose.

How Skypoint Recovery Helps

At Skypoint Recovery in Akron, our medically supervised Xanax detox gives you a team to get you through withdrawal safely. Our medical professionals monitor your symptoms and adjust medications as needed, so you aren’t facing the hardest days alone. After detox, our partial hospitalization program offers up to six hours of therapy on most days, and it helps people with co-occurring conditions like anxiety alongside substance use. If Xanax started as a sleep aid for you, our look at alprazolam for sleep explains the risks of that path, including dependence and withdrawal.

You don’t have to figure out the taper on your own. Reach out to our team to talk through your options confidentially.

Frequently Asked Questions

1. How long does Xanax withdrawal last?

The acute phase comes first, after you cut back or stop. Some people then have lingering anxiety, sleep problems, or trouble concentrating that can last weeks to more than 12 months. A gradual, supervised taper lowers the risk of withdrawal reactions.

2. Can you die from Xanax withdrawal?

Yes, it can be fatal in some cases. Stopping Xanax abruptly or cutting the dose quickly can cause life-threatening withdrawal reactions, including seizures. That’s why you should never stop suddenly after regular use.

3. When does Xanax withdrawal start?

It can start soon after your last dose. Xanax has an average half-life of about 11 hours, so the amount in your body drops quickly once you stop. Some prescribers switch people to a longer-acting benzodiazepine before tapering for that reason.

4. What helps with Xanax withdrawal?

The most effective step is a gradual taper planned with your prescriber, often with medical supervision if you’ve used it heavily. Support for the anxiety and sleep issues underneath, through therapy and structured treatment, helps you stay off it once the taper is done.

men at aa meeting

AA vs. NA: Which 12-Step Program Is Right for You?

The main difference between AA and NA is what they were originally built to address: Alcoholics Anonymous (AA) focuses on alcohol, while Narcotics Anonymous (NA) focuses on addiction to drugs more broadly. Both use the same 12 steps and the same basic meeting structure, and in practice, plenty of people attend both regardless of which substance was their primary issue. The right one for you usually comes down to which language and community feel like the closest fit, not a strict rule about what you’re allowed to attend.

If you’re trying to decide between them, or wondering whether it matters at all, here’s what actually separates the two and how people typically choose.

Where AA and NA Came From

Alcoholics Anonymous was founded in 1935 in Akron, Ohio, by Bill W. and Dr. Bob, two men who discovered that talking honestly with another alcoholic kept them both sober in a way that willpower alone hadn’t. That original meeting became the foundation for one of the most widely used frameworks for recovery, built entirely around mutual support between people with the same struggle.

Narcotics Anonymous grew directly out of AA, forming in 1953 when people whose primary addiction was to drugs, not alcohol, wanted a program that spoke their language more directly. NA adapted AA’s same 12 steps, replacing alcohol-specific wording with broader language about addiction, so the program would fit anyone struggling with substance use, not just drinking.

What’s Actually Different

Strip away the branding and the two programs are structurally almost identical. The differences that matter are smaller than most people expect:

  • Language and focus. AA speaks specifically about alcohol and “sobriety.” NA speaks more broadly about “addiction” and substance use of any kind, including alcohol.
  • Who tends to show up. AA meetings often have a higher concentration of people whose primary issue was drinking. NA meetings often include people with a wider range of substance histories.
  • Meeting availability. In many areas, AA has been around longer and has more meetings available, simply because of its head start and larger overall membership.
  • The steps themselves. Nearly identical. Both move through admitting powerlessness, taking a moral inventory, making amends, and eventually helping others, with the wording adjusted to fit alcohol versus addiction more broadly.

Both groups describe powerlessness the same way, as an honest acknowledgment that addiction is a serious opponent nobody beats entirely alone rather than a sign of weakness. And both leave the concept of a “higher power” open to interpretation. That can mean a traditional religious framework, the collective wisdom and support of the group itself, or something else entirely. Neither program requires a specific religious belief to participate or benefit.

So Which One Should You Go To?

A few honest questions can point you in the right direction:

  • Was alcohol your primary substance? AA meetings, language, and literature are built around that specific experience, which can make the fit feel more immediate.
  • Was your substance use broader than alcohol, or primarily drugs? NA’s language will likely feel more directly relevant to what you’ve actually been through.
  • Which meetings are actually available near you and when? In a lot of areas, especially smaller communities, meeting availability matters as much as which program technically fits best. A meeting you’ll actually attend consistently beats a theoretically perfect fit you skip.
  • Are you comfortable trying both? Plenty of people in recovery attend AA and NA interchangeably, especially if their substance use involved both alcohol and drugs. Nothing stops you from going to either, regardless of which specific substance brought you there.

There’s no wrong answer here. The advice most people in recovery will give you is to try a few meetings of each and pay attention to where you feel like you can actually be honest.

How 12-Step Support Fits Into a Full Recovery Plan

AA and NA are peer support programs, not clinical treatment, and they work best alongside professional care rather than in place of it. At Skypoint Recovery Ohio, 12-step principles are built directly into aftercare, woven into individual and group therapy so the connection to a sponsor and a peer community continues well past your last day of formal treatment. That combination, clinical treatment plus an ongoing peer support structure, tends to hold up better over time than either one alone.

If your history includes both alcohol and other substances, it’s worth knowing that our approach also incorporates AA’s 12-step framework alongside evidence-based tools like medication-assisted treatment, so the peer support side and the clinical side aren’t working against each other.

For a broader look at what aftercare includes beyond 12-step meetings specifically, our post on different types of aftercare services walks through the full picture of what keeps recovery strong once formal treatment ends.

Frequently Asked Questions

1. Can I go to AA if my primary problem was drugs, not alcohol?

Yes. AA meetings are generally open to anyone seeking recovery, though the language and shared experience in the room will be more alcohol-focused. Many people find NA’s broader language a more direct fit if drugs, not alcohol, were the primary issue, but attending AA isn’t off-limits.

2. Is NA just AA for drugs?

That’s a reasonable shorthand. NA was built directly from AA’s model and the 12 steps are nearly identical, just with broader language about addiction rather than alcohol specifically. The core approach, mutual peer support and working the steps, is the same.

3. Do I have to believe in God to do the 12 steps?

No. Both programs use the phrase “higher power,” and both leave that concept open to interpretation. For some people that’s a traditional religious framework. For others, it’s the support and collective experience of the group itself. Neither program requires a specific religious belief.

4. How long do people typically stay involved in AA or NA?

There’s no required length of time or formal graduation point. Many people stay involved for years, sometimes decades, as an ongoing part of maintaining their recovery, attending meetings as often or as rarely as fits their life at that point.

5. Can I attend both AA and NA?

Yes, and many people in recovery do exactly that, especially if their substance use involved more than one type of substance. There’s no rule limiting you to one program, and attending both is common practice, not an exception.

Whichever program feels like the right fit, the peer support side of recovery works best paired with real clinical care behind it. If you’re putting together a full recovery plan and want to understand how 12-step support fits alongside treatment, our admissions team can talk through what that could look like for you.

medical detox

What Actually Happens During Medical Detox? A Day-by-Day Guide

Medical detox is the process of clearing a substance from your body under 24-hour medical supervision, while trained staff manage the physical symptoms of withdrawal and keep you safe. It’s a medical process, not a therapeutic one. The goal is physical stabilization, not the deeper work of understanding why you use or building skills to stay sober, that comes next. 

If you or someone you love is about to walk into detox for the first time, not knowing what to expect is often the hardest part. Here’s a realistic, day-by-day look at how it typically goes.

Before Day One: Evaluation

Every medical detox starts with a comprehensive evaluation, not medication. A medical team reviews your health status, substance use history, and any co-occurring medical or mental health conditions. This is where staff ask what you’ve been using, how much, for how long, and what previous withdrawal experiences have looked like, since a history of severe withdrawal (including seizures) changes how closely you’ll be monitored.

This step matters because withdrawal from different substances looks nothing alike. Alcohol, opioids, and benzodiazepines like Xanax or Valium can all cause withdrawal that’s physically dangerous, including seizures and cardiac complications, so supervised medical detox for these isn’t optional. Stimulants like cocaine or methamphetamine, and cannabis, cause withdrawal that’s exhausting and uncomfortable but not usually medically dangerous in the same way. The evaluation determines which situation you’re in and how detox should be structured for you specifically.

Days 1-3: Withdrawal Symptoms Begin and Peak

This is usually the most physically intense stretch, and it varies significantly by substance.

Alcohol: Early symptoms like tremor, anxiety, sweating, and a racing heart rate can begin within 6 to 12 hours of the last drink. Some people experience hallucinations in the 12- to 24-hour window while remaining otherwise alert and oriented. Seizure risk peaks between 24 and 48 hours, and delirium tremens (DTs), the most dangerous stage, involving confusion, high fever, and severe instability, typically emerges between 48 and 72 hours for people at risk. This is exactly why round-the-clock monitoring matters so much for alcohol withdrawal specifically.

Short-acting opioids (like heroin or oxycodone): symptoms often start 8 to 12 hours after the last use and peak around 48 to 72 hours, with intense cravings, GI distress, and flu-like symptoms during this window.

Longer-acting opioids (like methadone): withdrawal starts more slowly, often 1 to 3 days after the last dose, and peaks later, generally 3 to 8 days out.

Throughout this stage, the medical team’s job is to manage symptoms safely while monitoring vital signs continuously. That typically means carefully prescribed medications, tailored to your specific substance use history and withdrawal presentation, adjusted as needed to keep you as comfortable and stable as possible. It also means round-the-clock nursing care and emergency response capability if something changes quickly, which it can.

Days 3-7: Stabilization

As acute physical symptoms start to ease, whether that’s day 3 or closer to day 7 depends heavily on the substance and your individual response, the focus shifts to stabilization. Vital signs level out, medication doses are adjusted downward as symptoms allow, and sleep, appetite, and mood begin to normalize, even if slowly. For opioid withdrawal from short-acting substances, most physical symptoms have typically cleared by 7 to 10 days, though psychological cravings can linger well beyond that. For longer-acting opioids, physical symptoms may persist for a few weeks.

This stage is also when the deeper conversation starts. Getting through the physical part of withdrawal means you’re stable enough to actually engage with the work ahead, and that work is still just beginning.

The Final Days: Preparing for the Next Level of Care

As physical symptoms stabilize, the team begins preparing you for whatever comes after detox, whether that’s residential treatment, partial hospitalization (PHP), intensive outpatient (IOP), or another level of care based on your clinical assessment. This is one of the most important parts of the entire process, and it’s also the part that’s easiest to skip if you’re detoxing without a connected treatment program behind it.

That gap matters. Detox alone, without follow-up treatment, has a well-documented high return-to-use rate. Clearing the substance from your body addresses the physical dependence, but it doesn’t touch the patterns of thinking, the emotional triggers, or the circumstances that made using feel necessary in the first place. That’s exactly why medical detox at Skypoint Recovery Ohio is built to connect directly into the rest of the continuum of care, so there’s no gap between getting physically stable and starting the real work.

We’ve written in more detail about how detox and rehab fit together, and why one without the other usually isn’t enough, in Detox vs. Rehab: What’s the Difference, and Do You Need Both? if you want to understand that connection more fully before you call.

Frequently Asked Questions

1. How long does medical detox take?

It depends on the substance and your health history. Alcohol detox often runs three to seven days. Short-acting opioid withdrawal typically resolves within seven to ten days, while withdrawal from longer-acting opioids like methadone can take a few weeks. A clinical team monitors your symptoms and adjusts the timeline based on how you’re actually progressing, not a fixed schedule.

2. What medications are used during medical detox?

It varies by substance and by person. Medications are chosen and dosed based on your specific withdrawal symptoms, substance use history, and overall health, then adjusted throughout detox to keep you safe and as comfortable as possible.

3. Is it dangerous to detox without medical supervision?

It can be, particularly for alcohol, opioids, and benzodiazepines, where withdrawal can involve seizures, dangerous changes in vital signs, or delirium tremens. Attempting to withdraw from these substances alone carries real medical risk, which is exactly why supervised detox exists.

4. What happens after detox is finished?

Detox is a starting point, not the finish line. Most people move directly into a structured level of care, residential treatment, PHP, or IOP, so the physical stabilization detox provides carries into the therapeutic work of understanding triggers and building a plan for staying in recovery.

5. Do I need detox before I can start rehab?

If you’re physically dependent on alcohol, opioids, or benzodiazepines, yes, it typically isn’t safe to start intensive rehab programming while you’re also managing acute physical withdrawal. If your substance use doesn’t involve that kind of physical dependence, a clinical assessment may determine you can move directly into treatment without a separate detox stage.

You don’t have to know exactly what your detox will look like before you make the call. A brief assessment through our admissions team can walk you through what to expect based on your own situation, and help you understand exactly what the days ahead would look like.

male alcoholic drinking shot at night

Signs You Might Need Dual Diagnosis Treatment

Dual diagnosis, sometimes called a co-occurring disorder, is when a mental health condition, like depression, anxiety, PTSD, or bipolar disorder, shows up alongside substance use, and treating one without the other hasn’t worked. It’s more common than most people realize, and it usually calls for a more integrated approach than treating either condition on its own.

Here’s what to look for, and why it usually takes a different, more integrated approach to treat.

What Dual Diagnosis Actually Means

Dual diagnosis simply means a substance use disorder and a mental health disorder are present at the same time, a description of the overlap rather than a diagnosis on its own. Someone with dual diagnosis might have depression and an alcohol use disorder, or PTSD and an opioid use disorder, or bipolar disorder and stimulant use. The specific combination varies, but the core issue is the same: two conditions that feed into each other, and neither one improves much if the other is left untreated.

This is more common than a lot of people expect. Research shows that roughly half of people who experience a substance use disorder at some point in their life will also experience a mental health disorder, and vice versa. Recent estimates put the number of U.S. adults with a co-occurring mental health and substance use disorder at approximately 7.7 million.

Signs You Might Be Dealing With Dual Diagnosis

No single sign confirms a dual diagnosis on its own. What matters is the pattern. If several of these sound familiar, it’s worth talking to someone who can do a real clinical assessment.

  • You use substances to manage a mental health symptom. Drinking to quiet anxiety, using to numb depression, or self-medicating racing thoughts or intrusive memories.
  • Your mood or mental health symptoms are extreme or unpredictable. Sharp mood swings, prolonged low periods, panic, or irritability that doesn’t match what’s going on around you.
  • You’ve had mental health symptoms before substance use started, or the two seemed to appear together. The order doesn’t matter clinically, but a connection between the two is a strong signal.
  • Previous treatment for just one issue didn’t hold. You got sober but the underlying anxiety or depression came roaring back, or you got mental health treatment but couldn’t stop using once you left.
  • You’re pulling away from people, work, or responsibilities. Social withdrawal, missed work or school, and difficulty concentrating can show up in both conditions and often compound each other.
  • You have a family history of either condition. A family history of mental illness or addiction raises the odds of both showing up together.
  • Thoughts of self-harm or suicide are part of the picture. This is a sign that needs immediate attention, not just a factor to weigh later.

Why Treating Only One Condition Usually Doesn’t Work

It’s tempting to treat whichever condition feels more urgent and deal with the other one later. In practice, this rarely holds up. Untreated depression or anxiety makes it much harder to stay in recovery, since the substance was often doing real (if harmful) emotional work that hasn’t been replaced with anything else. On the flip side, active substance use can mask, worsen, or mimic mental health symptoms, which makes an accurate mental health diagnosis difficult until substances are out of the picture.

This is why dual diagnosis treatment addresses both conditions together, in the same program, with a team that’s coordinating care rather than treating them as separate problems handled by separate providers who never talk to each other.

What Dual Diagnosis Treatment Looks Like

Effective dual diagnosis care is integrated, meaning the mental health and substance use treatment happen at the same time, from the same coordinated team, rather than one after the other. At Skypoint Recovery Ohio’s dual diagnosis program, that typically includes:

  • Medical detox and withdrawal management, when a substance use disorder requires it.
  • Individual, group, and family therapy to work through both the addiction and the mental health condition together.
  • Evidence-based therapies like cognitive behavioral therapy (CBT), motivational interviewing (MI), and dialectical behavior therapy (DBT), each suited to different aspects of co-occurring conditions.
  • Trauma-informed care, since trauma so often underlies both a mental health condition and substance use.

If trauma is part of your story, our team’s approach to trauma-informed addiction treatment is built specifically around that connection.

The goal isn’t just stopping substance use. It’s building a foundation where the mental health condition is also stable enough that substances stop feeling like the only tool that works.

Frequently Asked Questions

1. What is dual diagnosis?

Dual diagnosis describes having both a substance use disorder and a mental health disorder at the same time. It’s also called a co-occurring disorder. Neither condition is considered the “real” problem, both need treatment.

2. How common is dual diagnosis?

Very common. Research indicates about half of people who experience a substance use disorder in their lifetime also experience a mental health disorder, and current estimates put the number of U.S. adults with a co-occurring disorder above 20 million.

3. Can you treat a mental health condition and addiction at the same time?

Yes, and this integrated approach generally produces better outcomes than treating the conditions separately or one after the other. Studies show roughly half of people with co-occurring disorders respond well to combined treatment.

4. What happens if only the addiction is treated, and not the mental health condition?

The untreated mental health condition often drives a return to substance use, since it was frequently the reason the substance use started or continued in the first place. This is one of the main reasons standalone detox or rehab without a mental health component has a high return-to-use rate for people with a co-occurring condition.

5. How do I know if I need dual diagnosis treatment instead of standard rehab?

A clinical assessment at intake is the most reliable way to know for sure. If you’re experiencing ongoing mental health symptoms alongside substance use, especially if one seems to trigger or worsen the other, it’s worth raising directly during that assessment so both conditions are accounted for from day one.

If any of this sounds like what you or someone you love is going through, you don’t have to sort out which condition to address first on your own. Our admissions team can walk you through a confidential assessment and help you understand what integrated treatment could look like for your specific situation.